
knee joint pain treatment
Knee Joint Pain Treatment: How to Choose Your Next Step

Make the treatment decision a comparison, not a diagnosis made at home
Knee joint pain treatment is not one decision with one universally suitable answer. Your next step depends on how the pain began, how long it has lasted, whether you can bear weight, what other symptoms accompany it, what an examination shows, and what you want to discuss with a healthcare provider. The practical goal is to match the urgency and the question to the appropriate pathway rather than name a condition from symptoms alone.
An initial knee-pain evaluation should consider the pain’s location, onset, duration, quality, related mechanical or systemic symptoms, swelling, trauma, and relevant medical or surgical history. Those details help a clinician decide whether you need prompt attention, routine evaluation, rehabilitation-oriented care, imaging, an injection discussion, a regenerative discussion, or a conversation about other treatment categories. They do not provide a diagnosis by themselves.
AAOS guidance covers less-invasive alternatives to knee replacement and says care should reflect clinician judgment, your circumstances, values, preferences, and rights. The guidance is a reference rather than a fixed treatment protocol. Shared decision-making matters because the same label, such as knee arthritis, can still leave different questions about urgency, evidence, risks, practical limits, and personal priorities.
Use this guide to organize the next discussion. Start with safety, then describe the pain pattern, clarify what an evaluation is meant to establish, compare the broad pathways, and ask what is known and uncertain about any injection or regenerative option. That sequence keeps a treatment conversation connected to your actual knee rather than to a treatment name alone.
Your first decision is the timeline: immediate attention, prompt medical evaluation, or a planned discussion. After that, your symptoms and examination findings can narrow the next question. No pathway should be selected solely because it sounds newer, less invasive, or more familiar.
Screen for symptoms that change the timeline
A knee injury with a deformed joint, a popping noise, inability to bear weight, intense pain, or sudden swelling calls for immediate medical attention. Severe pain, swelling, instability, or inability to bear weight after acute trauma also warrants prompt medical evaluation. Do not use a home treatment plan as a substitute for urgent assessment when one of these patterns is present.
These symptoms warrant a medical visit, and the combination of fever, swelling, redness, and limited motion is a reason for prompt evaluation because signs of joint infection may require urgent attention. Contact an appropriate medical service rather than waiting to see whether routine self-care changes the pattern.
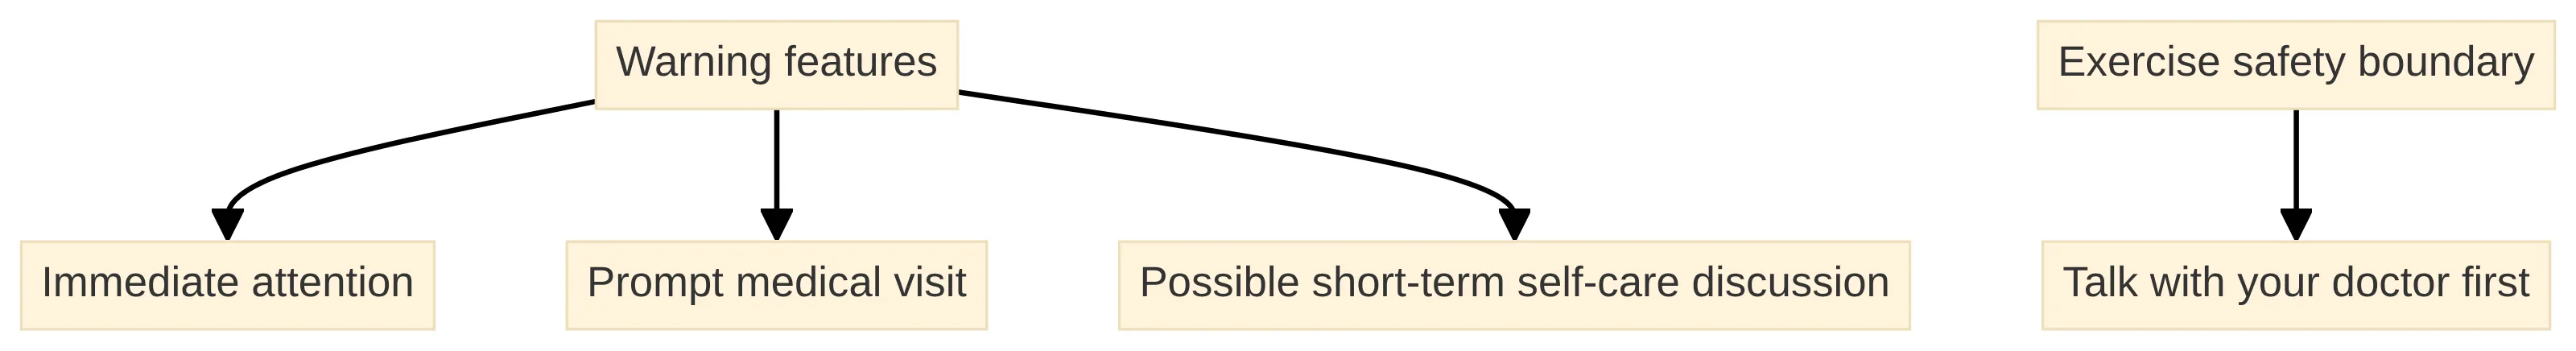
Use the following boundary when deciding what to do next:
- Immediate attention: A deformed knee, a popping noise, inability to bear weight, intense pain, or sudden swelling after an injury.
- Prompt medical visit: A forceful impact, significant swelling, redness, tenderness, warmth, significant pain, or fever around the knee.
- Possible short-term self-care discussion: Gradual pain, a minor injury, or pain after more strenuous activity when the concerning features above are absent.
The third category is not a diagnosis or a promise that home care is appropriate for you. It is a limited circumstance in which gradually developing pain, pain after a minor injury, or pain after more strenuous activity can sometimes be managed at home with over-the-counter pain relievers and RICE self-care.
Exercise deserves its own safety boundary. Talk with your doctor before starting any exercise program, particularly if pain, swelling, instability, or reduced function has not been evaluated. A plan that is reasonable for a gradually developing symptom may be unsuitable after trauma or when the knee is becoming harder to move or load.
Bring the pattern of pain to an evaluation
The pattern of knee pain gives an evaluation its starting information. Before an appointment, write down:
- Where the pain is located and whether it stays in one area or spreads.
- When it began, whether the onset was sudden or gradual, and how long it has continued.
- What the pain feels like and what activities change it.
- Whether swelling, locking-type mechanical symptoms, instability, or other systemic symptoms occur.
- Whether trauma, a change in activity, or a prior medical or surgical history may be relevant.
This record does not diagnose the cause. It gives the healthcare provider a clearer account of what has changed and helps keep the discussion focused.
A clinical evaluation generally connects your history with an examination. A clinical review describes inspection, palpation, range-of-motion and strength assessment, neurovascular testing, and special tests as parts of a systematic knee examination. Osteoarthritis care may also involve different professionals, including primary-care doctors, rheumatologists, orthopaedic surgeons, physical therapists, occupational therapists, dietitians, and physiatrists.
The appropriate professional depends on the question that needs answering. You may begin with primary care, discuss rehabilitation with a physical therapist, or seek an orthopaedic assessment when the symptoms, history, or prior evaluation make that relevant. The point is not to collect opinions without a purpose; it is to identify which clinical question remains unresolved.
Persistent knee pain deserves a planned evaluation rather than indefinite trial and error. A clinical review describes chronic knee pain as lasting more than six weeks for purposes of considering radiographic imaging, although the decision still depends on the clinical question and the circumstances of the pain. If your pain continues, worsens, or changes your walking, work, sport, sleep, or daily activities, bring those functional effects to the appointment. Describe the sequence rather than only the worst day: note when the change began, what activity preceded it, whether swelling or instability appeared, and whether the limitation is improving, stable, or worsening. This gives the healthcare provider a time-based account to place beside the examination and relevant history. It also helps distinguish the question of urgency from the separate question of which treatment categories deserve discussion. A persistent symptom still requires clinical context; duration alone does not identify its cause or determine whether imaging, rehabilitation, an injection discussion, or another pathway is appropriate.
Ask your healthcare provider to explain what the evaluation suggests, which uncertainties remain, and what decision the next test or treatment is meant to support. AAOS guidance describes care as dependent on clinician judgment and your circumstances, values, preferences, and rights. That makes your goals part of the discussion, not an afterthought.
Use testing to answer a clinical question
Testing is most useful when it answers a defined clinical question. A clinical review of knee pain says radiographic imaging should be reserved for chronic knee pain lasting more than six weeks or for acute traumatic pain that meets specific evidence-based criteria. The timing and purpose of a test should stay connected. If pain has lasted more than six weeks, ask whether imaging would clarify the problem being considered and how the result would affect the options under discussion. After an acute injury, ask which examination findings or trauma features make imaging relevant. The priority may be an urgent assessment, a focused examination, or monitoring for a change in symptoms rather than a scan. A test can provide information without resolving every uncertainty, so ask what the healthcare provider will do with either result. Separate the question of whether a test is relevant from the question of which treatment you prefer. Interpret a result alongside the pain pattern, examination, function, and priorities described elsewhere in this guide. That does not mean every painful knee needs imaging immediately, and it does not mean an image alone determines the treatment path.
Before a test, ask what the clinician is trying to clarify and how the result could change the discussion. Useful questions include:
- What finding are you looking for?
- Which symptom or examination finding makes this test relevant?
- What would a normal or abnormal result change?
- Are there other reasons to seek prompt care while waiting?
AAOS guidance says clinical practice guidelines are reference and educational tools rather than fixed protocols. A clinician should apply independent judgment to your circumstances rather than use a testing rule as a substitute for assessment.
Your symptoms still matter after testing. Imaging may contribute information, but the decision conversation must connect the result with your history, examination, function, and priorities. If the clinical question is unclear, ask for that question before treating a test result as a treatment recommendation.
Compare the established non-surgical starting points
Non-surgical starting points can serve different purposes, so compare what each pathway is meant to clarify or support rather than treating them as interchangeable. The AAOS knee osteoarthritis guideline summary addresses less-invasive alternatives to knee replacement. Its recommendations are intended to be considered with clinician judgment and your circumstances, preferences, and rights.
In joint replacement care, lifestyle discussions may include nutritional counseling, weight loss programs, and exercise. Talk with your doctor before starting any exercise program. No general lifestyle category should be turned into an individualized prescription without an evaluation. One useful distinction is between a pathway that manages a current symptom and an evaluation that clarifies what is happening. Self-care or rehabilitation discussions may focus on function and day-to-day limits. Imaging, an injection discussion, or a regenerative consultation should be tied to a clinical question and the findings that make that question relevant. A surgery-related discussion likewise depends on the evaluation rather than on a general assumption that persistent pain leads to surgery. The same person may discuss more than one category over time, but the categories should not be treated as interchangeable promises. Ask which information is already known, which uncertainty remains, and what change in symptoms or findings would alter the next conversation. This keeps the comparison anchored to your circumstances, values, preferences, and rights rather than to the name of an option.
| Pathway to discuss | Question it can address | Boundary for your next step |
|---|---|---|
| Short-term self-care | Is the symptom pattern limited enough for cautious home management while you watch for change? | Use this only where concerning features are absent; seek care if the pattern changes or warning signs appear. |
| Rehabilitation-oriented care | Could a physical therapist or another clinician help assess or work on joint function? | Discuss the exercise or activity plan with a doctor before beginning an exercise program. |
| Lifestyle discussion | Could nutrition, weight, or activity be relevant to the wider joint-care conversation? | Ask for advice suited to your health and knee rather than adopting a general program on your own. |
| Injection discussion | Is an injection being considered for a clearly defined clinical question? | Ask what evidence, benefit, uncertainty, and procedural risk apply to the specific injection. |
| Regenerative discussion | Does a physician-led regenerative evaluation address the question you want to explore? | Treat the consultation as an evaluation of relevance, not as a promise of pain relief or tissue change. |
| Surgery-related discussion | Does your evaluation raise a question about options beyond less-invasive care? | Ask the clinician to explain why that discussion is relevant to your findings and priorities. |
Rehabilitation may involve physical therapists, who help improve joint function, and other professionals may contribute when osteoarthritis affects nutrition, daily activities, or broader physical functioning. A surgery-related conversation is not an automatic conclusion; it is a question to raise when your clinician believes the less-invasive pathways under discussion do not answer the clinical problem.
Shared decision-making keeps these categories connected. Ask which option is being considered, what it is intended to do, what alternatives remain, and what would cause the plan to change.
Choose the next discussion by matching the pathway to the unresolved question. If the question is safety, seek evaluation. If it is function, discuss rehabilitation. If it is whether an injection or regenerative approach is relevant, ask for evidence and risk information specific to that option.
Let response and priorities shape the next conversation
Your response to an initial pathway can guide the next conversation, but response alone does not confirm a diagnosis. Track changes in pain, swelling, motion, stability, walking, work, sport, sleep, and daily activities in terms you can describe. Tell your healthcare provider whether the change was absent, partial, temporary, or accompanied by a new concern.
AAOS guidance says treatment should be based on independent clinical judgment and individual circumstances rather than a fixed protocol. A response record gives the clinician useful context for deciding whether to continue the discussion, modify it, or reconsider the working question.
Your priorities can change which trade-offs deserve attention. You may need to discuss the importance of returning to a particular work task, walking a certain distance, participating in sport, limiting time away from work, avoiding an invasive procedure, understanding cost, or knowing how much uncertainty you are willing to accept. State the priority plainly and ask how each proposed pathway relates to it.
The AAOS guideline summary identifies your circumstances, values, preferences, and rights as part of treatment decisions. That principle supports an open conversation without turning a personal priority into proof that one treatment will work.
Use these questions when a first approach has not answered your concern:
- What changed in my symptoms or examination?
- What does that change make more or less likely?
- What is the purpose of the next option?
- What evidence supports it for a knee with this pattern?
- What risks, costs, time demands, or uncertainties should I weigh?
- What finding would make us stop, change direction, or discuss another pathway?
Shared decision-making works best when the plan and its boundaries are explicit.
Place injections and regenerative options in an evidence-aware comparison
Injections are procedures, not a single treatment category with a single level of evidence. A 2025 Cochrane review found that, compared with placebo injections and based on low-certainty evidence, stem-cell injections for knee osteoarthritis may slightly improve pain and function. The review was uncertain about effects on quality of life, treatment success, structural progression of the knee, and safety.
That finding supports a careful discussion, not a guaranteed result. Ask which injection is being considered, what condition and outcome the evidence addresses, how closely your situation matches the studied population, and what remains uncertain.
Joint injections carry a small risk of septic arthritis, and the review says other important harms remain unknown for the stem-cell intervention it assessed. Ask about procedural risks, expected monitoring, alternatives, and what symptoms after an injection should prompt medical attention. Do not treat a regenerative label as a substitute for a risk discussion.
A combination protocol is a discussion about using more than one regenerative modality within a physician-led plan. Ask what each component is intended to address, why the combination is being considered for your knee, what evidence supports the components, and how the plan would be evaluated. The name of a protocol does not establish that it is suitable for you or that it will produce a particular outcome.
Keep the comparison concrete:
- Evidence: What outcome has been studied, and how certain is the evidence?
- Fit: What finding makes this option relevant to your knee?
- Procedure: What will happen, and what risks accompany an injection?
- Uncertainty: What remains unknown about benefit, safety, or longer-term effects?
- Alternatives: What established or less-invasive pathways remain available?
- Decision point: What would make you continue, pause, or choose another discussion?
This framework helps you compare a treatment conversation without turning limited evidence into a promise.
Ask what is known, uncertain, and relevant to your knee
Evidence has to be read with its conditions attached. The 2025 Cochrane review’s stem-cell finding concerns knee osteoarthritis, compares stem-cell injections with placebo injections, describes possible small improvements in pain and function, and rates the evidence as low certainty. It does not establish a general result for every cause of knee pain, every regenerative product, or every person.
AAOS guidance likewise functions as a reference rather than a fixed protocol. Ask how a recommendation applies to your diagnosis or working assessment, the findings from your evaluation, your goals, and the alternatives you are considering.
Uncertainty should be specific rather than treated as a vague warning. For stem-cell injections, the review reports uncertainty about quality of life, treatment success, structural progression, and safety. Ask which of those outcomes matters most to you and whether the available information answers that particular question.
The responsible next step is to identify the benefit being considered, the evidence behind it, the procedural risks, and the limits of what can be predicted. To judge relevance, separate the condition studied from the condition being evaluated, the outcome measured from the outcome you care about, the comparator from the alternative you are considering, and the certainty of the evidence from the confidence of a particular recommendation. In this case, the review concerns knee osteoarthritis, compares stem-cell injections with placebo injections, discusses pain and function, and reports low-certainty evidence. If your clinical question differs, ask the healthcare provider to explain what can and cannot be carried over. A treatment conversation should leave those boundaries visible rather than turning a limited result into a general expectation.
Bring these questions to an injection or regenerative consultation:
- What is the working diagnosis or clinical question?
- Which outcome are we trying to influence: pain, function, motion, or something else?
- What evidence applies to that outcome and to my knee?
- How certain is the evidence?
- What risks and unknowns should I weigh?
- What alternatives can we discuss before deciding?
- What would count as a meaningful change and when would we reassess?
Shared decision-making means you should have enough information to weigh the choice with the clinician.
Assess whether a physician-led regenerative evaluation fits the question
At our Ohio practice, we provide non-surgical knee, hip, and shoulder care. Our service context includes patients in Ohio and Chicago, so you can ask whether an evaluation near those locations addresses the question you want to explore.
A regenerative evaluation may fit your question if you have persistent or concerning knee pain and want a clinician-guided discussion of non-surgical options, evidence, procedural risks, and alternatives. It is not a substitute for urgent care when you have a deformed knee, inability to bear weight, intense pain, sudden swelling after injury, fever, or other warning features. Address the timeline first.
Our physician-led service includes stem cell therapy, exosome therapy, peptide therapy, and combination protocols, with ultrasound or fluoroscopic guidance used for image-guided precision injections. If regenerative treatment is unlikely to help your joint, we provide an honest assessment and direct you to what will help. That boundary makes the evaluation a discussion about fit, not an assurance that a procedure will be recommended.
We offer free consultations for knee, hip, or shoulder pain. We are a self-pay practice and do not bill insurance for regenerative treatments. Ask about the financial terms before making a decision, and keep cost alongside clinical relevance, evidence certainty, procedural risk, and alternatives in your comparison.
If your symptoms are persistent or concerning and you want to discuss whether our non-surgical knee services fit your question, request an evaluation. Bring your symptom pattern, prior testing, treatment history, goals, and the questions about evidence and uncertainty listed above.
Prepare a treatment-comparison checklist
A knee-pain treatment checklist gives you a practical record to use during an appointment. Write down:
- The exact location, onset, duration, and quality of the pain.
- Any swelling, instability, reduced motion, mechanical symptoms, fever, or other symptoms.
- The injury, activity change, or event that preceded the pain.
- What you can and cannot do at work, during sport, while walking, or during daily activities.
- Relevant medical or surgical history.
- Tests, treatments, exercises, or medications already discussed with a healthcare provider.
- Your main goal for the next stage of care.
Use the checklist to keep the appointment decision-focused:
- What is the main clinical question right now?
- Does the symptom pattern require immediate, prompt, or routine attention?
- What did the examination establish, and what remains uncertain?
- Is testing being recommended to answer a specific question?
- Which non-surgical pathways are reasonable to discuss?
- What outcome is each option intended to address?
- What evidence, risks, costs, and unknowns apply?
- What would change the plan?
AAOS guidance says treatment should reflect clinician judgment and your circumstances, values, preferences, and rights. These questions help make those factors visible.
If you are considering regenerative care, add three specific prompts: What evidence applies to my knee and the outcome I care about? What procedural risks and unknowns should I weigh? What are the self-pay costs, and what alternatives should I discuss first? A 2025 Cochrane review found low-certainty evidence for possible small improvements in pain and function from stem-cell injections for knee osteoarthritis, while reporting uncertainty about several other outcomes and safety. Our regenerative treatments are self-pay and are not billed to insurance.
Keep the completed checklist with your medical records and use it to compare what each clinician recommends. Its purpose is to organize your symptoms, questions, priorities, and decision boundaries. It does not determine eligibility, select a procedure, or predict an outcome.
Choose the next discussion, not a guaranteed outcome
The right next step for knee pain starts with timing, then moves through evaluation, testing when a clinical question supports it, non-surgical pathways, injections or regenerative options, and surgery-related discussion when your findings make that relevant. Warning signs change the timeline, persistent symptoms deserve evaluation, and treatment choices should reflect your circumstances, preferences, risks, and goals. A qualified healthcare professional should decide individual suitability with you.
If you are near Ohio or Chicago and want to discuss persistent or concerning knee pain with REGEN Orthopedic Medicine, our physician-led non-surgical services include stem cell therapy, exosome therapy, peptide therapy, and combination protocols. We offer free consultations, and our Ohio practice provides non-surgical knee care using stem cells, exosomes, and peptides. Bring your symptom record and ask for a clear comparison of relevance, evidence, uncertainty, risks, alternatives, and practical terms.
Free consultation
Find out whether regenerative treatment is right for you.
Most consultations begin as a telehealth call with a physician specialist, so you can start without travelling to a clinic. No referral needed.